
Hardware Removal After Ankle Surgery: What to Know (and What to Expect)

This is before my hardware came out. The curved plate and the screws attaching it came out about six weeks ago, but the screws on the other side are still there. You’ll find the picture of my ankle sans hardware below.
Why does this damn thing still hurt, could the hardware be causing it, what happens if I have it taken out, and will I actually feel better afterward?
FROM THE TRENCHES
Here are some actual experiences from my fracture friends.
One woman went into hardware removal and ankle arthroscopy 14 months after her original bimalleolar fracture absolutely terrified. She remembered the agonizing pain after ORIF and expected another version of the same thing. Instead, she was allowed to bear weight immediately. She left the hospital using two crutches, was down to one briefly that first night, and although she still needed crutches and pain medication during the first week, she described the pain as nothing like the original surgery. Around Day 11, something shifted: walking became easier. Her stitches came out at two weeks, and she was ready to concentrate on physical therapy and getting back the range of motion she had lost.
For another patient, hardware removal provided something besides physical relief: validation. For months, she had insisted that her hardware was causing her pain, even though some of her doctors questioned it. She also had numbness in two toes and part of her foot, with pins and needles when she rubbed near one of the screws. When the hardware came out, she said the pain disappeared almost immediately. Sensation began returning to her foot as well. She was walking the next day, had only incision pain for the first few days and, two weeks later, had been cleared to return to her job as a construction laborer.
Then there was the woman who had two titanium plates and 18 screws after shattering her tibia, fibula and ankle in a ladder accident. Two years later, despite faithfully working on strength and mobility, she still had pain and only about 40 percent of her normal ankle motion. Her surgeon eventually agreed to remove the hardware. A few months afterward, she estimated that her range of motion had improved to nearly 90 percent of her other ankle. She was back in the gym running, jumping and skipping rope—and, perhaps just as importantly to her, wearing high heels again. The hardware itself? She kept it in a jar.
One athlete celebrated a different milestone five weeks after hardware removal: her first pain-free box jump in more than a year. After a trimalleolar fracture and dislocation, she had spent much of the previous year wondering whether her mobility would ever return. There had been no obvious problem with the hardware on imaging; she simply felt that something wasn't right. Five weeks after removal, she was jumping again and working toward her old 30-inch box jump.
Not every story was uncomplicated. One person had hardware removed while her surgeon was already operating to clean out scar tissue and repair a bone chip. The initial recovery was easy and was expected to involve only a few quiet days followed by stitch removal at two weeks. Instead, an infection appeared about three weeks after surgery and took roughly two months to resolve.
That last story is worth keeping beside all the success stories. Hardware removal may be a much smaller operation than the surgery that put the hardware in, and some people recover remarkably quickly. But it’s still surgery. The experiences range from almost immediate relief to weeks of recovery—and occasionally to complications nobody planned on.
The Fracture Healed. So Why Would You Volunteer for Another Surgery?
That’s the question at the heart of hardware removal. Plates, screws and other fixation devices are put in for a reason: to hold broken bones in position while they heal. Once the fracture is solid, the hardware may quietly stay in place for life. For some people, though, the bone heals and the ankle still doesn’t feel right.
A plate may sit where a shoe rubs. A screw may be prominent under thin skin. Hardware can irritate nearby soft tissue, and pain may be very localized over a plate or screw. Other people describe stiffness, tenderness, swelling, cold-weather sensitivity or simply the persistent sense that they can feel the hardware.
Hardware removal is therefore not automatically the next step after an ankle fracture heals. The more useful question is whether the hardware is actually causing a problem—and whether removing it has a reasonable chance of solving that problem.
How Common Is Hardware Removal?
It’s common enough that you are certainly not an oddity if you end up considering another operation, but there is no single meaningful percentage that applies to everyone. Studies report very different removal rates because surgeons, countries, implant types and reasons for removal differ. One large ankle-fracture study of 997 patients found that 17% eventually had their implants removed, most often because of patient complaints.
The important point is not the exact percentage. Modern practice is generally selective: hardware that is doing its job and causing no trouble is often left alone, while symptomatic hardware may be considered for removal after the fracture has healed.
Why Is Hardware Removed?
Common reasons include:
· Pain or tenderness that seems to correspond with a plate, screw or other implant.
· Prominent hardware that rubs against shoes or is uncomfortable beneath the skin.
· Irritation of nearby tendons or other soft tissue.
· Infection or concern about infection involving the hardware.
· Loose, migrated or broken hardware, or another mechanical problem.
· Occasionally, suspected metal sensitivity after more common causes of symptoms have been considered.
Pain after a healed ankle fracture isn’t automatically hardware pain. Arthritis, scar tissue, tendon injury, nerve irritation, impingement and other consequences of the original injury can produce similar complaints. That distinction matters because taking out a perfectly innocent plate will not fix a different problem.
Will Removing It Actually Help?
Sometimes, considerably. But this is one of those questions for which the research gives a range of answers rather than a guarantee.
In one study of 80 ankle and distal-tibia cases, average pain scores fell from 3.4 before removal to 1.3 afterward; about 81% of patients were satisfied, and many reported less stiffness and less discomfort walking on uneven ground. A newer study of hardware removal at multiple orthopedic sites found that about 74% of respondents reported improvement in pain and 87% said their overall status improved.
Other research is more sobering. In an older ankle-fracture study, only half of the patients who had hardware removed for lateral ankle pain reported improvement in that pain. A 2024 lower-extremity study likewise found that people whose main complaint was specific pain were much more likely to be satisfied than people seeking removal for vague or nonspecific discomfort.
The takeaway? Hardware removal can help, particularly when the symptoms have a clear relationship to the hardware, but it isn’t a reset button for every ache, limitation or bit of stiffness left behind by a serious ankle fracture.
What Does the Surgery Involve?
Hardware removal is usually an outpatient procedure. The surgeon generally works through the previous incision or incisions, locates the implants and removes the screws, plates or other hardware. Anesthesia may be general, regional or a combination depending on the procedure and the patient.
The phrase “hardware removal” makes the operation sound almost mechanical: open the old incision, take out the screws, close it up. Sometimes it really is fairly straightforward. Sometimes it isn’t. Scar tissue can make hardware harder to expose, screws can be difficult to remove, and nearby tendons, nerves and soft tissues may need attention. If another source of pain has been identified — such as impingement or scar tissue — the surgeon may address that during the same operation.
Ask exactly what your surgeon expects to do besides removing metal. Two people can both say they are having “ankle hardware removal” and undergo very different operations.
Don't Assume This Recovery Will Be Nothing
Compared with the original ORIF, hardware removal may be a smaller operation. That doesn’t make it no operation at all. There is still an incision, surgical trauma, swelling and healing to get through.
Weight Bearing and Protection
Postoperative instructions vary widely. Some patients are allowed to bear weight as tolerated almost immediately, sometimes in a boot or postoperative shoe. Others are protected for a period of time because of the amount or location of hardware removed, the condition of the bone and soft tissues, or additional work performed during surgery. Your surgeon's plan outranks somebody else's recovery story.
The Incision
The wound needs the same basic respect as any surgical incision. Dressings are generally kept clean and dry, and sutures are commonly removed around 10 to 14 days after surgery. Soaking usually waits until the incision has healed and your surgeon has cleared it. Yup, that means no pool time.
Pain and Swelling
Soreness and swelling are expected, particularly during the first days and weeks. Elevation, icing when permitted, prescribed or over-the-counter pain medication, and not getting too ambitious too quickly may all be part of the early plan. Swelling can outlast the period when the incision looks healed.
Motion, Physical Therapy and Activity
Gentle ankle motion may begin early in some protocols, while other surgeons impose temporary restrictions. Formal physical therapy is not automatic after every removal, but it may be useful when stiffness, weakness, gait problems or additional soft-tissue work are part of the picture. Return to work, driving and sport depends less on a universal calendar than on what was removed, which ankle was operated on, what else was done and how well you’re functioning.
Driving deserves particular caution after right-ankle surgery. Being able to walk is not the same as being able to make a fast, forceful emergency stop. You also shouldn’t drive while impaired by narcotic pain medication.
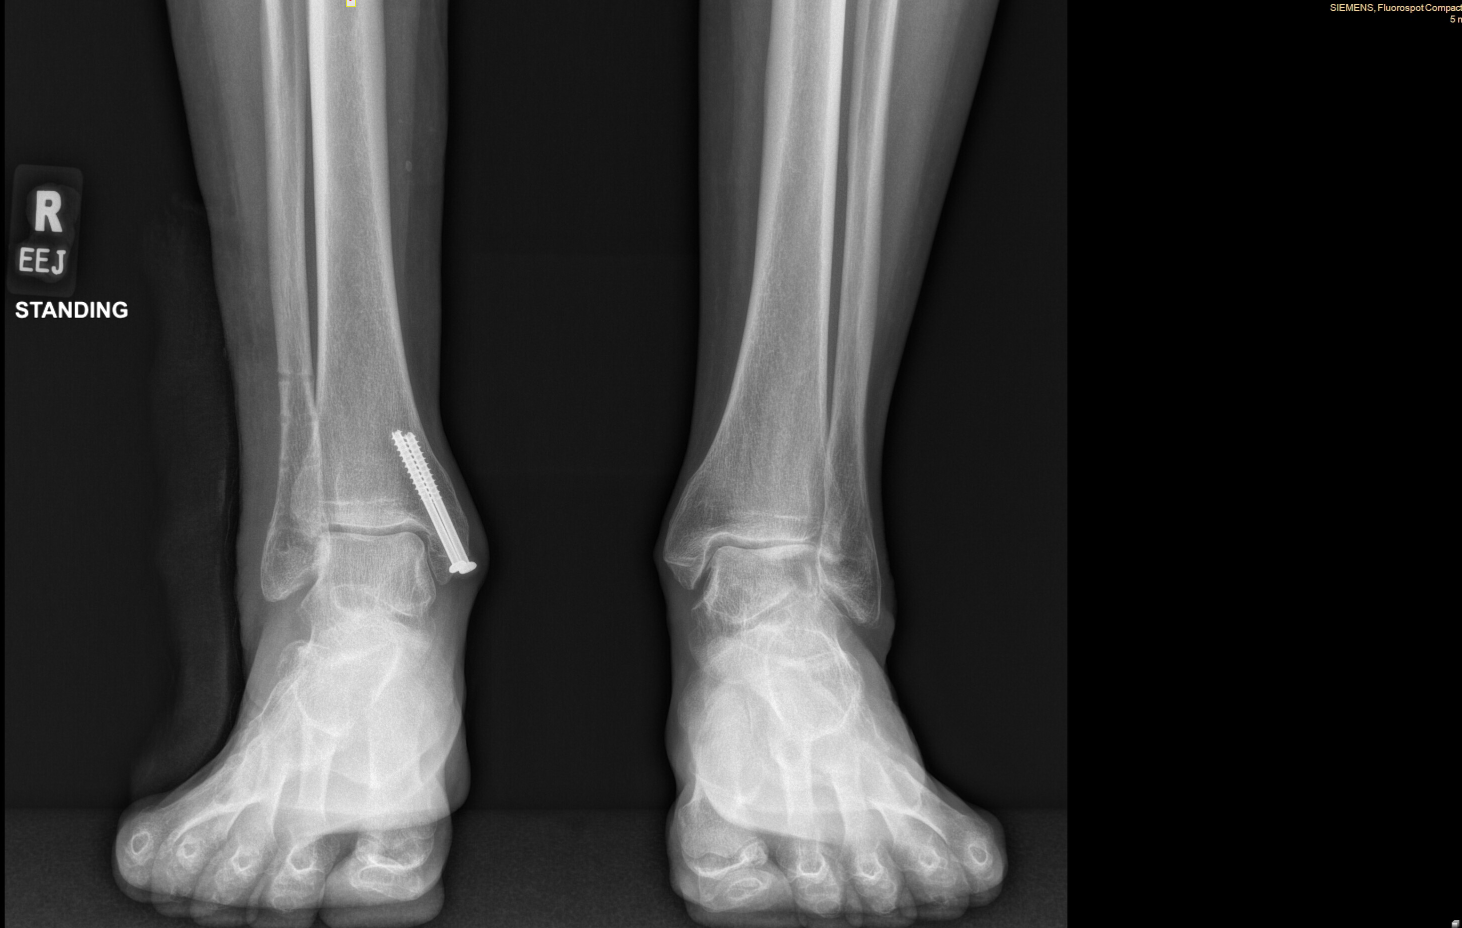
This is my ankle, two weeks post op, after the plate and screws holding it came out. Look at the holes in the bone!
The Holes the Screws Leave Behind
When a screw comes out, the bone doesn’t instantly become exactly as it was before the screw went in. A screw tract remains and gradually fills in with new bone. During that period, the area can be temporarily weaker. Orthopedic surgeons sometimes describe a screw hole as a “stress riser” — a place where forces can concentrate rather than spreading evenly through the bone.
That does not mean the ankle is waiting to snap. Refracture after hardware removal is uncommon, but the temporary change in bone strength is one reason surgeons may restrict impact, twisting, jumping or other high-load activities for a period after removal. The amount of caution needed depends on the size, number and location of the screw holes, the bone involved, bone quality and the activities you want to return to.
This is especially worth discussing if your definition of “back to normal” includes running, jumping, riding, heavy physical work or another activity that puts considerably more force through the ankle than walking around the house.
I was appalled when I saw my X-rays two weeks post op. No wonder my surgeon wanted me to stay off of my horse! My leg had a line of holes through the bone. Apparently, the greatest risk for re-fracture is the first few weeks.
What Can Go Wrong?
Hardware removal has real surgical risks even when it is elective and relatively straightforward. Reported complication rates vary with the patients and procedures studied. One ankle-specific series reported perioperative complications in 14% of 80 patients; a newer study of percutaneous hardware removal reported a 5.5% complication rate. The numbers are less important than understanding what the complications can be.
· Wound-healing problems or infection.
· Nerve irritation, numbness or nerve injury.
· Bleeding or hematoma.
· Difficulty removing all of the hardware.
· Persistent pain because the hardware was not the only source of symptoms.
· Rarely, refracture or another mechanical problem.
Risk is individual. Smoking, circulation problems, diabetes, poor soft-tissue condition, multiple incisions and a more complicated operation can change the picture. The fact that hardware removal is common doesn’t make it trivial.
NOBODY TOLD ME...
Hardware removal is not simply ORIF played backward. The fracture may be healed, but the operation still creates a new injury that has to heal. And removing the metal does not erase everything the original fracture did to the joint, tendons, nerves and soft tissue.
The other surprise is how much the recovery instructions can differ. One patient may walk immediately; another may spend time in a boot or on crutches. One may need little rehabilitation; another may have additional tendon or scar-tissue work that changes the timeline completely. Comparing yourself with someone who merely had one accessible screw removed can be wildly misleading if you had a plate, multiple screws and soft-tissue work.
Just like I shouldn’t have been comparing myself to my doctor friend.
MY TAKE ON IT
I had a doctor friend who had her hardware out about a week before I did-- Daina. A week after her surgery—though she admitted doctors are the worst patients and that her surgeon would “kill her if he knew”—she was back riding her horse.
The layup time is one of the worst parts of surgery for me, so naturally I was excited. My surgeon planned to put me in a cast, non-weightbearing for two weeks, but said I could use the leg as tolerated after that. I naturally assumed I would immediately be back on my horses, as well, being likewise tough and a bad patient (even though I’m not a doctor).
The pain immediately after my surgery surprised me. To say it was intense is an understatement; it was a nine out of 10. I ended up getting a ‘rescue block,’ that is, an ultrasound-guided popliteal sciatic nerve block that kept my leg numb for about 18 hours—just like I had in my initial ORIF surgery, except after the fact.
I was terrified that the pain would be unbearable after the block wore off, but it wasn’t too bad. I controlled it with elevation, ice, Tylenol and ibuprofen.
After the first two weeks, when my cast came off, I anticipated being set free to do my normal activities. Apparently, my surgeon didn’t realize my normal activities go beyond sitting behind a desk and walking. She was adamant that I not ride my horses. The whole thing—the hassle, the pain, the stiffness and weakness afterwards, the rehab—was excruciatingly familiar, though definitely easier than the first time around.
That being said, I would have the surgery again. While it turned out my plate wasn’t interfering with anything, the scar tissue around my peroneal tendon was “severe,” making it impossible for my tendon to glide. If it hadn’t been removed my recovery would have always been limited.
My point is to measure the decision carefully. Hardware removal is still surgery, and it isn't necessarily a miracle cure. In my case, the hardware wasn't even the real problem. But surgery gave my surgeon the opportunity to find and remove the severe scar tissue that was preventing my peroneal tendon from moving normally. I didn't get the answer I expected. But I still got a good answer.
WORTH KNOWING
The best predictor of a satisfying result may not be how badly you want the hardware gone, but how clearly your symptoms can be tied to it. Specific pain over prominent or irritating hardware gives the surgeon a more concrete target than a general sense that the ankle has never felt normal.
Before deciding, make sure the conversation includes the possibility that something else is contributing to the problem. If the answer is “we think the plate is irritating the tendon,” that’s very different from “we don't know why it hurts, but we can take the plate out and see.”
ASK YOUR SURGEON
· What makes you think my symptoms are coming from the hardware rather than arthritis, scar tissue, tendon or nerve problems, or something else?
· Exactly what are you planning to remove, and do you expect to do any additional work on tendons, scar tissue or the joint?
· What will my weight-bearing and activity restrictions be, and how long do you want me to avoid impact, twisting, running, jumping or other high-load activity?
· What improvement do you realistically expect — and which symptoms might remain even if the surgery goes perfectly?
Sources / Working References
· Jung HG, et al. “Is Hardware Removal Recommended after Ankle Fracture Repair?” BioMed Research International. 2016. PMID 27819005.
· Brown OL, et al. “Incidence of hardware-related pain and its effect on functional outcomes after open reduction and internal fixation of ankle fractures.” Journal of Orthopaedic Trauma. 2001. PMID 11371792.
· Minkowitz RB, et al. “Removal of painful orthopaedic implants after fracture union.” Journal of Bone and Joint Surgery American. 2007. PMID 17768185.
· Page BJ, et al. “Percutaneous removal of hardware after orthopedic surgery: Is it safe? and What are patients saying?” European Journal of Orthopaedic Surgery & Traumatology. 2024. PMID 38981919.
· Schmidutz F, et al. “Patient satisfaction after elective implant removal of the lower extremity - a retrospective cohort study.” 2024. PMID 38319352.
· Kasai T, et al. “Complications of implant removal in ankle fractures.” Journal of Orthopaedics. 2019. PMID 30906121.
· Naumann MG, et al. “Incidence and risk factors for removal of an internal fixation following surgery for ankle fracture: A retrospective cohort study of 997 patients.” Injury. 2016. PMID 27262772.
· Kim HN, et al. “Arthroscopy combined with hardware removal for chronic pain after ankle fracture.” Knee Surgery, Sports Traumatology, Arthroscopy. 2013. PMID 23179450.